Wednesday, January 26, 2022

May 2003 to July 2019 immigrant and citizen conflict over health services for poor people misplaces blame twice


    The full page in the picture above from a public library microfilm collection of out-of-business local newspapers, and the column pictured below, blame immigrants for the problems of poor and disabled citizens accessing primary and specialized health services that private health insurance won't pay for.  Medicare and Medicaid are constrained by taxpayer greed.  The article correctly points out that the wealthy  are less harmed by immigration than poor and disabled citizens.  Wealthy people have benefited from regressively lower effective top marginal income tax rates that have been reduced, since the 1950's, by tax cuts of mostly Republican presidents and Congressional majorities under Presidents Reagan, W Bush and Trump. 


   By 2012 the author of this 2003 column in the out of business Montgomery/Prince George's Journal and Express had been quoted citing a link between living with a mental health disability and poverty. 


To paraphrase Randy Bosin, a peer/survivor advocate and NAMI member … “no economic recovery for peer/survivors, no wellness!” To which I would add that the problem is one of economics and the social stigma that’s attached to unemployed and poor people; accordingly, the solution is political. More on this below.

That a relationship exists between poverty and mental illness was first established in the landmark New Haven study conducted by Hollingshead and Redlich (10), whose findings were published in 1958. Their principal conclusion was that there is a significant relationship between social class (SES or socio-economic status) and mental illness as regards the type and severity of the illness suffered as well as the type and quality of the treatment provided. Specifically, persons who were members of the lowest social stratum were the poorest, had a higher incidence of presumed serious mental illness and received the least adequate forms of treatment if they received any treatment at all. What was not clear was the direction of their findings, i.e., which phenomenon, mental illness or poverty, preceded which. 


   The unfortunate division of poor and working class people based on national origin and citizenship or immigration status from 2001 to 2003 in Maryland's largest county would occur again in 2019.  The Disability Integration Act was being lobbied for by activists at the same time as the Trump administration was cruelly separating children from parents of undocumented immigrants.  The cruel law enforcement policy was an attempt to deter immigration rather than deal with the root causes of immigration.  The Disability Integration Act was the third legislative attempt to codify the 1999 Olmstead vs LC and EW supreme court decision after the failure of the CLASS Act by 2012.


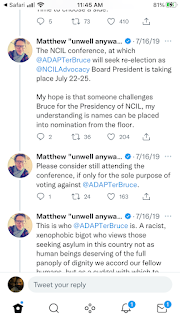
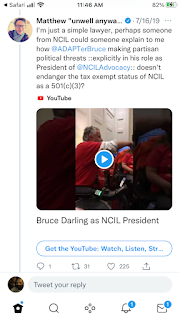
  Bruce Darling a leader of ADAPT was forced out of his NCIL position after he claimed that Democratic party members of congress MOCs care more about undocumented immigrants [deleted tweet screenshots of deleted tweets below]


than citizens with disabilities. 


 One of the activists there was Bruce Darling from Rochester, the Executive Director of that city’s Center for Disability Rights (CDR) and the Board President of the National Council on Independent Living (NCIL). Darling is a long-time and highly visible ADAPT organizer. Another was Dawn Russell, also a very experienced and well-known leader, from Denver. Also present was Dara Baldwin, a D.C.-based disability leader who works for CDR and has played a key role in coordinating the disability community’s efforts on passing the DIA. As is ADAPT’s custom, activists posted a livestream on the National ADAPT Facebook page and an audience watched from home.
While the group was in Representative Eshoo’s office, Darling made statements that attracted attention. About 14 minutes into the video, he said, “Our talking point is, ‘Democrats care more about people who are not legally in this country than their own citizens who are disabled.’ It really is what the message is here. That basically [pointing to different disabled activists] you and you and you and you, you are less than. You are not worthy. We are more concerned about immigrants who happened to come here in a non-legal manner than we are with our own citizens, and we will lock disabled people up. This is going to be the message from the dais at the [NCIL] conference. This is not what Democrats want. It’s not what we want.” Viewers in the disability community began to contact their friends. “Are you watching ADAPT? Did you see what Bruce said?” The group was gone from Eshoo’s office by the time I was alerted to the video, and several of my friends and I discussed what to do. Eventually, I tweeted. I may have been the first to do so or I may have just been the first to be seen by people whose retweets were widely read. I said that Darling had “suggest[ed] that disabled people with and without citizenship are in a competition for justice” and that he was “speaking on my behalf without my consent.” I denied that he – or anyone – had the authority to say that in my name.


    More deleted tweets from @mattbc here that followed the first two tweets in a thread.  In addition to calling out the racism in what Bruce Darling said, dividing people with disabilities by national origin and immigration status, @mattbc was protecting the 501c3 status of the NCIL from challenge by demanding Bruce Darling be removed from a board and encouraging people to vote him out of the NCIL presidency. 


     Bruce Darling repeated the same 2003 talking points dividing poor and working class people by the protected classes of disability, national origin and immigration status.  Bruce Darling failed to connect issues of poverty that intersect with civil rights law protected classes like disability, race and national origin/immigration status that are related to poverty as well as Randall Bosin did between 2003 and 2012.

  Most of the activism that demanded the Disability Integration Act, as well as the Community Choice and CLASS Acts, has coalesced around the caregiving funds in the Build Back Better reconciliation covid19 relief bill that has been cut from $250 Billion to $150 Billion.  Opposition from D WV Joe Manchin and D AZ Kyrsten Sinema to passage has stalled BBB and its caregiving funds perhaps for the rest of the 2022 second session of Congress that ends in January 2023.  

2001-3 Mental and Primary health clinic closures for underinsured residents and documented and undocumented immigrants


   The increased population from immigration, documented (legal) and undocumented (illegal), has strained the budgets of state and local governments without adequate federal government help.  "Drama" (conflict) has disrupted activist movements that build communities of people to advocate the interest of constituencies within the communities.  


  In Montgomery County, Maryland in the recession of 2000 to 2003 population increases due to immigration led to a division between advocates of 'safety net' services for people with mental illness who were uninsured or underinsured citizens and documented and undocumented immigrants.  

  Short term grants were given here and described in this article


Council OKs $695,000 for mental health clinics
 
By Karl Hille
Montgomery Journal staff writer
Wednesday, October 17, 2001
 
The Montgomery County Council Tuesday granted $695,000 to bail out nine mental health clinics that are experiencing difficulties under increasingly complex federal Medicaid and Medicare payment provisions and shrinking state funding.
 
The grant raises to $870,000 this year the county's stake in a mental health care system council members insist is not a local government responsibility.
 
``In this area, it is clear to me the federal government ignores its responsibility, the state takes piecemeal responsibility and the county is left to make Band-Aid solutions," said Council President Blair G. Ewing, D-at-large.
 
The grant includes a $20,000 base allotment to each clinic to cover administrative costs. The rest of the money will be distributed based on the number of patients relying on public insurance coverage who come for treatment.
 
To receive the support, the clinics agreed to a management audit by the county Department of Health and Human Services, to work with the agency to determine how to measure its performance and to continue appropriate treatment for patients who enter county jails or homeless shelters.
 
Clinic operators said the grant would allow them to continue serving patients already in their care, but almost none of the clinics operating in the county will take on new patients either dependent on Medicare or uninsured.
 
``We have been forced to choose between survival and complete dedication to our mission ... to serve the people who need us the most," said Jeff Carzwell, vice president of marketing for Affiliated Sante Group, one of the nine clinics.
 
Federal Medicare coverage for seniors covers only 50 percent of psychiatric services, and providers say many who depend on the federal system cannot afford to make up the difference.
 
Pam Cudahy, director of St. Luke's House in Bethesda, said this one-time grant will help the clinics survive this year only.
 
``Unless there is change at the state and federal level, we believe the [reimbursement] rates will continue to be inadequate over a period of time," she said.
 
Evelyn Burton, spokeswoman for the Montgomery chapter of the National Association for the Mentally Ill, said the alternative would be to deny treatment to many county residents.
``These funds are needed today to prevent clinic closure," she said. ``There is currently no public clinic to serve as a safety net for the long term needs of English-speaking adult consumers who may be denied treatment by private clinics because they are uninsured or underinsured."
 
Burton also said requiring clinics to extend their services to jailed patients could have ``dire financial and organizational consequences" if the clinics do not receive an additional grant.
 
``These are services that are not reimbursable by Medicaid," she said, ``and were not contemplated in the calculation of the grant requested by the clinics."
 
Randall Bosin, a mental health advocate, supported the grant, though he said the grant agreement did not guarantee strong enough protections for existing patients.
 
``It would be good if the subsidy is tied to certain trackable, concrete commitments the providers are required to make," he said.
 
He said the county ``poured out" money last year for a similar grant to keep the Chestnut Lodge clinic in Rockville open for a few extra days. The clinic, which offered care to the mentally ill, eventually closed.
 
Bosin also said the need for these services could increase.
 
``There's evidence already that we are going to have increased requirements of these services since Sept. 11," he said.


  The crisis continued into 2002 a state and local election year as well as a 'midterm' federal election 2 years after a presidential general election.


https://health.maryland.gov/newsclippings/archives/2002/apr02/041902.htm#General%20Assembly%20failed%20many%20ailing%20Marylanders

[copy and paste in case link has died]

`Dire shortage' strikes mental health clinics
 
By Whitney L. Jackson and Karl Hille
Montgomery Journal staff writers
Friday, April 19, 2002
 
Two privately run mental health clinics will no longer take new patients, despite efforts by Montgomery County to keep clinics operating.
 
Washington Assessment and Therapy Services in Silver Spring and Affiliated Sante Group in Wheaton announced they do not have the resources to treat a growing number of patients coming to their doors for help.
 
``Since December we have just been overrun with people who need treatment because we were the only place where they could find that," said Jeff Carswell, vice president of corporate development for Affiliated Sante Group.
 
The clinic, which is located in the Mid-County Service Center on Reedie Drive, currently serves about 1,151 patients. Since December, the clinic has been accepting 75 to 100 new patients a month, Carswell said.
 
The clinic also absorbed many of the patients from the closing of CPC's Chestnut Lodge in Rockville last April, Carswell said.
 
Susan Wynne, site manager of Washington Assessment and Therapy Services, told the County Council that they too have a ``dire shortage of psychiatric coverage" at a public hearing Tuesday night.
 
Council member Blair Ewing, D-at-large, proposed adding $645,000 to the county budget to assist mental health clinics.
 
The $645,000 allocation includes $100,000 for Medicare, underinsured and uninsured clients, $100,000 to pay for care management at the clinics, and a $75,000 independent assessment of the clinics.
 
Many clinic representatives have said they need a lot more money to stay in operation. They have said the state privatized its mental health-care system in 1996, but private providers have had difficulties getting payment for older patients under Medicare, and handling the large amount of paperwork they say is needed to get payment from the state.
 
The Montgomery County Council allocated $870,000 in emergency funds in October 2001 to help the county's nine clinics keep their doors open, and the county executive and state health department announced an additional $1 million in reallocated funds in January tied to reform
measures.
 
Many clinic operators, however, said while the emergency appropriations from the County Council helped, government processing has kept most of the funds from reaching their target.
 
Carswell said Affiliated Sante Group only received $90,000 of the $140,000 they billed the county, and Threshhold Services in Silver Spring said they would close their doors permanently in March and Montgomery General Hospital closed their Colesville clinic in February.
 
``The County Council has been really supportive, but it takes so long for the money to get to the providers," Carswell said.
 
Affiliated Sante Group, which is the largest mental health provider in the county, employs about 13 therapists and four physicians.
 
Ewing blamed the county's Department of Health and Human Services for stonewalling and opposing the current proposed allocation.
 
``The Department of Health and Human Services didn't send comments or show up" to the public hearing, Ewing said. ``They said the funds are unnecessary and current funding is adequate."
 
David Weaver, spokesman for County Executive Douglas M. Duncan, said the appropriations already passed should be adequate to keep clinics open temporarily, but the rest of the burden should not fall on the county.
 
``We do not believe Montgomery County taxpayers should be the funders of first resort for mental health," Weaver said. ``It's very clear in this current environment that the state needs to do even more. ... This is a state responsibility and the state needs to meet its obligation."
 
Ewing said the shortage of clinics taking new patients could discourage mentally ill individuals from seeking treatment.
 
``People with serious mental illnesses won't be able to get treatment anywhere," he said. ``If it's made harder to get into a clinic, their willingness to pursue treatment could go down."
   
Journal staff writer Kelly Smith contributed to this article.


  Ultimately Montgomery County could only afford to support primary health clinics for non-English speaking people (immigrants both documented and undocumented) in need.   

 [no link available Montgomery Gazette closed in 2015 and took their links down as well]

 County looks at money to aid upcounty clinics
 
By Sean R. Sedam
Montgomery Gazette Staff Writer
Wednesday, July 2, 2003
 
The executive director of the Spanish Catholic Center says the nonprofit needs county money in order to continue providing medical care to uninsured residents when the center's Gaithersburg clinic closes next week.
 
That money would be used to bolster medical services at the center's Langley Park clinic, which could take on more patients when the Gaithersburg clinic closes July 10.
 
"There is absolutely no consideration or plan to close or curb services in the Langley Park clinic, either in the adult clinic or in the pediatric clinic," said the Rev. Donald F. Lippert, who directs the Spanish Catholic Centers in Gaithersburg, Langley Park and Washington, D.C. "But we need continued support of the county in order to do it."
 
The County Council's Health and Human Services committee, in a closed session Monday, discussed giving money that would have gone to the Gaithersburg clinic solely to Langley Park, said George L. Leventhal (D-At large) of Takoma Park, who chairs the panel.
 
"At this point we're going to agree to award funds to Langley Park because the closure of Langley Park would be so devastating that we cannot afford the impact," he said.
 
Last month the Spanish Catholic Center's board of directors decided to close the Gaithersburg clinic, citing its rent and salary costs. The center's 13 employees were notified June 11 that they were to begin preparing to close the clinic. As many as nine employees, including the manager of the Gaithersburg and Langley Park centers, were told they would be laid off.
 
The Langley Park clinic, which serves 1,200 patients, is one of eight clinics to which Gaithersburg's 850 patients are being routed through letters, phone calls and announcements on Spanish-language television and radio.
 
But during the public portion of Monday's hearing, Leventhal voiced reservations about giving the Spanish Catholic Center any more taxpayer money, saying representatives of the center, which is affiliated with the Archdiocese of Washington, D.C., had not been candid with the County Council.
 
The council increased support to the clinic in this year's budget, earmarking up to $160,000 all told for the Langley Park and Gaithersburg clinics. The clinics provide routine examinations, preventive care, diagnosis and early treatment for low-income, uninsured residents.
 
"Had we known that such a closing was imminent, we would not have committed so much county funding to the Spanish Catholic Center," Leventhal said.
It is up to the county's public health chief, Lynn Frank, to decide whether the Spanish Catholic Center will keep all of that money now that Langley Park will be its sole medical clinic in the county. She is expected to make a recommendation to the council within the next two weeks.
 
The county had considered redistributing the money from the Gaithersburg clinic to others in the upcounty, including Mercy Health Clinic in Germantown, Proyecto Salud in Wheaton, Community Clinic in Gaithersburg and Mobile Medical Care.
 
But representatives of those clinics said they did not need the extra money to care for 25 Gaithersburg patients the county projects that each could see, Frank said.
 
The county pays about one-third of the operating costs of the clinics. The county will review how Gaithersburg's patients are distributed among the remaining clinics to determine how much each will receive in taxpayer money.
 
"It's hard to predict exactly what those clients are going to do," Frank said.
 
People will go where they are comfortable, she said, "whether that is the faith-based Mercy clinic or the strong Latino culture of Proyecto Salud."
 
The Department of Health and Human Services will provide Spanish interpreters to clinics that see an increase in Spanish-speaking patients, she said.
 
The Gaithersburg clinic will remain open through July 25 for patients to pick up their records. Any unclaimed records will be saved at the center's Washington headquarters.
 
Mobile Medical has offered to bring its van for six months to the center's Gaithersburg site on 117 N. Frederick Ave. for walk-in patients, Frank said.
 
The center's social service referral program will be discontinued along with the clinic, but officials are looking to reopen elsewhere in Gaithersburg with its employment, immigration and English classes.
 
Council members on Monday asked whether the clinic's closing could have been avoided.
 
Lippert sent two letters to Leventhal in April informing him of the center's financial difficulties and indicating that the center may be forced to close.
 
The Gaithersburg and Langley Park clinics faced a combined $155,000 deficit when Lippert took over in April. He is the center's fourth director in four years. Gaithersburg's share of that deficit was about $80,000, Lippert said.
 
The center expects to save about $350,000 by closing the Gaithersburg clinic, finding another site for the center's classes and legal clinic and reducing staff at its Washington headquarters, he said.
 
The organization spent $3.5 million to operate centers in Gaithersburg, Langley Park and Washington in fiscal 2003, he said. A Wheaton center that included a medical clinic closed in 2002.
 
Last year the county gave the center $120,500 to operate between the Gaithersburg and Langley Park clinics and earmarked an additional $40,000 for the centers in fiscal 2004, which began Tuesday.
 
But more was needed.
 
"Our Board of Directors, executive director and medical director are looking very seriously at closing down some of our medical clinics and/or services due to severe funding shortages," Lippert said in an April 23 letter to Leventhal.
 
But Leventhal said he did not know how grave the situation facing the Gaithersburg clinic was until last month.
 
"This whole notion that this was a complete surprise was something that completely threw me off," Lippert said Tuesday.
 
Leventhal, who called the clinic's closing "the most serious matter I've had to take up as chairman of this committee," said Tuesday that he responded with a letter informing the center of the additional $40,000 the county was giving the clinics.
 
In a tight budget year when many nonprofits are asking for additional county help, he said, the center's voice may not have been loud enough.
 
"I don't think that we considered his letter to be a sign that they were about to shut down," Leventhal said.
 
At Monday's hearing, Leventhal told Lippert that the way the center handled the clinic's closing undercut his confidence in the center.
 
"It is the obligation of a public agency to be very transparent, not to surprise us," he said. "And that obligation has been very much violated, I think, in this case."


   The state of Maryland failed to help the largest county in Maryland pay to keep its safety net mental health and primary care clinics open for services. 


https://health.maryland.gov/newsclippings/archives/2002/apr02/040302.htm#Plan%20to%20Boost%20Psychiatric%20Clinics%20Dies


[copy and paste in case link has died]


Plan to Boost Psychiatric Clinics Dies
Md. Bailout Would Have Raised Taxes, Lawmakers Say
 
By Matthew Mosk
Washington Post Staff Writer
Wednesday, April 3, 2002; Page B02
 
Maryland lawmakers said yesterday that they have rejected plans to give a financial boost to the state's strapped psychiatric clinics and hospitals, because doing so would have required raising taxes.
 
The decision means lawmakers will emerge from the 2002 General Assembly session next week with no firm resolution to Maryland's mental health crisis, advocates for the mentally ill said yesterday.
 
"Unfortunately, it's going to keep getting worse, and there's no relief in sight," said Herbert Cromwell, executive director of Community Behavioral Health Association of Maryland Inc. "I think you can expect to see more of a meltdown."
 
Thirteen outpatient mental health clinics and private psychiatric hospitals have closed in the past four years, forcing patients out on their own, sometimes with dire consequences. In particular, emergency rooms have had an influx of urgent psychiatric cases in every corner of the state, state health officials say.
 
When legislative leaders convened in Annapolis in January, they vowed to solve what they agreed was a health crisis. Midway through their 90-day session, they found untapped federal funding that would immediately direct $40 million to shore up a $70 million deficit in the mental health budget.
 
But yesterday, with a week left before they break for the year, lawmakers said they will opt against a measure that advocates say is far more important -- one that channels more money to the financially troubled clinics. The roughly $45 million needed to pay for that effort was to come from a 2 percent tax on the income health maintenance organizations raise through premiums.
 
"Someone has decided they don't want it," said Sen. Edward J. Kasemeyer (D-Baltimore), who sponsored a bill creating the tax and directing it to mental health. "I think it's a dumb political move, but there's not much I can do about it."
 
The Senate approved the tax, but House leaders have balked. With lawmakers poised to raise the state cigarette tax, several said yesterday that they feared the political consequences of voting for an additional levy.
 
"I don't think anyone wanted to move toward another new tax this session," said Del. Sheila Ellis Hixson (D-Montgomery), who chairs the House Ways and Means Committee. "I'm not sure the bang is worth the buck."
 
Strong opposition to the tax came from lobbyists for HMOs and small businesses, which had no interest in swallowing the added cost of the tax.
 
Lobbyist Ellen Valentino, an aggressive opponent of the tax, said the independent businesses she represents in no way objected to the goal of more funding for mental health. They just did not believe the responsibility for those costs should fall to them.
 
"There have been decisions not to properly fund mental health, not just this year but over a number of years," Valentino said. "The question is: Who should pay for that?"
 
Indeed, money problems have plagued Maryland's mental health program since 1997, when the state changed the way it reimburses clinics and hospitals for the care they give uninsured and Medicaid patients. Budget analysts estimate that the system faces a $20 million deficit this year; next year, that could grow to $70 million.
 
Maryland's crisis mirrors troubles in dozens of states that have experimented with managed care to pay mental health costs.
 
Maryland Health Secretary Georges C. Benjamin said yesterday that lawmakers and the governor have made improvements to the mental health system and that additional federal funding will help reduce the department's budget shortfall.
 
"But I think we all recognize that there's a lot of work yet to be done," Benjamin said. "The problem is, in this time of sacrifice, we couldn't afford to do all that we would have liked."

    A prior Montgomery County policy to privatize its public mental health system to nonprofits (NGOs) that subsidize public money with individual donations incentivized by tax deductibility was undermined when even the individual donors became 'fiscally challenged.' The generous individual donors had to reduce or cut their donations as individual incomes, even high incomes, dropped in 'bad business cycles/economies/recessions.'


https://health.maryland.gov/newsclippings/html/newsarchives061401.html#Another%20disaster%20looming%20for%20mental%20health%20care

[copy and paste again in case link has died]


Another disaster looming for mental health care?
 
Montgomery Journal Commentary
Thursday, June 14, 2001
 
Once again Montgomery county officials, with some exceptions, are fiddling around while vitally needed mental health services for thousands of county residents with serious mental illnesses are in flames. The refusal of the County Council (save Isiah Leggett, Derick Berlage and Phil Andrews) to support council President Ewing's plan to save Chestnut Lodge Hospital is the latest instance of this county government failing to respond to a crisis arising largely from its own misguided policies and negligence.
 
Starting in the early 1990s, the County Council began moving the county toward the privatization of mental health services - something County Executive Doug Duncan also supported - [a]nd making this the county's policy in 1994. Reductions in county funding for mental health during this period, especially dramatic in 1994, signaled this intent.
 
This policy began to be implemented in 1997, with the hasty recruitment of CPC Health, the county's largest private mental health provider and owner of Chestnut Lodge, with incentives of temporary subsidies and free rent, to take over the county's Wheaton clinic.
 
County officials tried to allay concerns about this transition, raised at the time by me and many others, including Gov. Parris Glendening, by assuring that CPC was a stable, longstanding provider that would offer the same level and continuity of care as the county clinics. These concerns were dismissed notwithstanding an awareness that private providers were struggling with drastically reduced payment rates under a new state funding system.
 
Moreover, by 1997 CPC was already beset with financial and organizational problems, according to Paul Williams, president of the medical staff, writing on behalf of 30 staff members in a local newspaper. CPC was $4 million in debt from its purchase of Chestnut Lodge the previous year, according to former CEO, Steven Goldstein, who cited this debt as the chief reason for the company's bankruptcy.
 
The county either failed to properly vet CPC or it knowingly handed over this - and subsequently, another - clinic to a troubled organization while making assurances to the contrary.
 
Elected and appointed county officials disingenuously claimed (and still do) that the likely loss of approximately $1 million in revenue under the new state system forced them to divest the county's clinics. They argued that under the new system the county could not ``afford to stay in
the mental health business.''
 
However, the county will spend less on mental health for the upcoming fiscal year than it did in 1994 or 1997, despite an increase in the operating budget of approximately $900 million, or 50 percent, and a doubling of the Health and Human Services budget, under which mental health falls, since 1994. Clearly, other priorities, both within and without HHS, were affordable. The state's changeover to a managed-care system became the convenient excuse for politicians to do what they had been intending for years.
 
The county washed its hands of its clinics and didn't look back. It failed to monitor, as mandated by the state, or address CPC's deteriorating financial situation and consequent disruptive impact on treatment over the past three-plus years. Even with subsidies and free rent, CPC's clinics were ``barely breaking even,'' according to their former clinical director. Once the subsidies ended, the clinics began running deficits, exacerbating the company's financial woes.
 
When CPC declared bankruptcy last fall, county officials merely offered assurances of a ``contingency plan'' in the event CPC went under. Had they exercised adequate and timely oversight, CPC's difficulties could have been addressed long ago, and Chestnut Lodge's demise
averted. Their failure to do so compounded the initial, inadequate vetting of CPC, thereby contributing to its downfall.
 
County officials evade responsibility by blaming CPC's demise, with some justification, on the company's mismanagement and a flawed state funding system, while excusing the privatization, even though all of the county clinics transferred to other private providers are also losing money, as are most outpatient clinics in the county.
 
Furthermore, they claim they couldn't have known about the internal problems of private providers like CPC, despite meeting monthly with representatives from these organizations since the privatization began for just this purpose.
 
Representatives, CPC's included, say they repeatedly told county officials of their organizations' plights. However, if county officials couldn't properly monitor CPC, why then, at times of great uncertainty, did they turn county clinics over to such a troubled provider? Moreover, if their assertions are correct, then it was necessarily unwise and irresponsible to privatize the clinics while promising to oversee the process.
 
In the current, hasty transition of CPC's clients to other struggling providers, the same officials are offering the same, meaningless reassurances about ``a smooth transition'' and ``minimal disruption of services'' as they did in 1997. Yet many unanswered questions remain about this transition, which is already proving to be problematic.
 
Responsible officials must acknowledge and learn from the mistakes that led to the CPC fiasco to avoid repeating it, including an understanding of the privatization's role and its inherent dangers. Only such an honest appraisal, coupled with pro-active vigilance will prevent similar catastrophes in the future.
 
Randy Bosin, of Chevy Chase, is an advocate for the mentally ill and a member of the National Alliance for the Mentally Ill. 
[later renamed National Alliance on Mental Illness]

Tuesday, November 9, 2021

inequitable pace of positive change can turn people against a movement


I shared my thoughts on @autismgadfly Jonathan Mitchell's motivations at the end of this post written in 2017 I shared with @Samanticka a year later,

 @Samanticka
I wrote this post about acceptance v cure last year. Shorter message: who pays costs of acceptance & inclusion & can all pay & receive to decent living standard? https://selfadvocacyskepticism.blogspot.com/2017/03/social-acceptance-goal-of-autism.html?m=1

12:43 PM · Jan 23, 2018·Twitter for iPhone

 in 2018, led to this twitter conversation. @slooterman joined in and replied too but both account controllers have since deleted their tweets.   Screenshots replace links because of tweet deletions since 2018. 

 @slooterman in the first 3 screenshots divided views of individual critic of neurodiversity movement, autismgadfly, as his personal views, unrelated to failure to find adequate LTSS in HCBS in his community, while centering most intense needs autistics in neurodiversity-informed activism demands.  @slooterman divided an autistic community from an autistic constituency by supporting the status quo of organizing a larger community to advocate for a smaller constituency.   Since 2011 autistic self-advocacy as done by ASAN partnered with the intense needs/low functioning ID/DD (formerly MR) group Self Advocates Becoming Empowered SABE.  Activism followed model with more inclusive rhetoric.  Being able to drive, afford a car and live alone in an apartment still without a job is not a fully independent life.  @autismgadfly is blaming the activists not the legislators of one party, Republican, who balk at spending any money for domestic discretionary programs.  That reluctance leads activists/self advocates to narrow the community into a smaller constituency with demands for more funding for LTSS delivered in HCBS. 


@slooterman replied to my account @nyr194 agreeing with me that private contractors are not better than public services.  The link she posted is inaccessible by twitter but one troubled ID group home contractor has rebranded after being exposed.


I also posted this to try to understand @autismgadfly's anti-neurodiversity and pro-cure (or what @autismgadfly means by a cure for his autism) politics. 

 This was one of the replies posted by autismgadfly. 

 @autismgadfly
·
Jan 25, 2018

but, yes, the post claiming I came to these conclusions due to bad financial circumstances and being left behind is absolutely false and typical of the dishonest statements ND's constantly write.

  Twitter account @lauralovesian1 replying “You are free to express your views” is condescending and a backhanded compliment.  @autismgadfly is 'Free to express' as long as others never agree making him an ‘influencer’ or persuasive.  If @autismgadfly views become persuasive then others feel entitled to attack gadfly by calling the views problematic then bigoted (ableist).


@slooterman wrote this column


 Some words on special needs moms in horror movies
The Babadook and other updates

Sara
Oct 12 [2020]


Heads up, folks: This week’s newsletter is about the portrayal of filicide in fiction. There is some very graphic description of filicide, and ideas about filicide. There are also spoilers for The Babadook.

In October, we watch horror movies.
COVID-19 may have prevented me from seeing my family for the Jewish High Holidays, but it can’t prevent me from a cherished tradition with my partner. I love horror movies. I wasn’t allowed to watch them as a kid — My mother was concerned about violence in media — So they’re forbidden fruit. Part of the pleasure is the sense of transgression. I’ve been living independently for years, but watching a horror movie still feels very much like I’m getting away with something.
Most recently, I saw The Babadook for the first time. And it may be one of the most disturbing horror movies I’ve ever seen. There are a lot of murderous mothers in horror movies. In The Conjuring, for example, an evil spirit possesses a mother in order to induce her to kill her own children. These stories are presented in stark moral terms. Killing one’s own children is seen as the ultimate evil, something that could only come from demonic influence or a cartoonish sort of mental illness.
But that’s not the case in The Babadook. In The Babadook, we’re encouraged to empathize and understand why a woman might be driven to kill her own child. This isn’t just my own interpretation of the film — The director, Jennifer Kent, has been fairly explicit about it.
"Now, I'm not saying we all want to go and kill our kids, but a lot of women struggle. And it is a very taboo subject, to say that motherhood is anything but a perfect experience for women."
In The Babadook, a mother, Amelia, is having a very difficult time. Her husband died driving her to the hospital. Her son, Samuel, has significant behavioral issues — He screams, makes makeshift weapons, talks endlessly about monsters, and is occasionally violent. He wakes her almost every night, so she hasn’t gotten much sleep. While there is no explicit reference to a condition like autism or ADHD, his behavior is painfully familiar. Amelia is exhauasted, sleep deprived, and struggles at work. Her sister rejects Samuel, and by extension, rejects Amelia. And the viewer is drawn deeper and deeper into sympathizing with Amelia.
Amelia has little support, but she also actively pushes support away. In one of the earliest scenes in the movie, Samuel’s teachers suggest that Samuel get a 1-to-1 aide. Instead, Amelia pulls him out of school. Amelia’s neighbor, a kind old woman named Gracie Roach, offers kind words and to even let Samuel sleep over. But Amelia refuses. She stops going to work. Slowly, Amelia and Samuel become more and more isolated, as they are hunted by a monster called the Babadook. Amelia, exhausted and terrified, becomes more and more violent, eventually killing the family dog before attempting to kill Samuel.
Many other critics have interpreted the Babadook to be a representation of grief — It is impossible to get rid of the Babadook. Instead, the Babadook, and by extension, grief, is something you have to learn to live with. But I think the Babadook is also embodied, murderous ableism. And while I’m disturbed by Jennifer Kent’s assertion that this is a tAbOo we should talk about, I appreciate that the Babadook is not portrayed as normal. Not everyone has a Babadook. Not everyone disabled has a Babadook. The neighbor, who has Parkinson’s, doesn’t have a Babadook. The seniors confined to the dementia ward where Amelia works don’t have a Babadook. The Babadook isn’t seen as natural or as an inevitability, and I appreciate that. Ultimately, Amelia does not kill her son. Instead, she learns to live with her darker impulses, without letting them consume her.


 on her substack page that rustedaspie (I) subscribed to from May 2020 until she deleted it in August 2021.  


  Although he will likely deny the point, @autismgadfly has a Babadook against neurodiversity and self-advocate operated organizations because he didn’t get the accommodations or supports to hold a job that Sara Luterman got.  Getting inclusion, acceptance, LTSS in HCBS and reasonable accommodations (paid for by one or more levels of government because individuals cannot pay the full cost) help people with disabilities drop their individual Babadooks.  Neurodiversity self advocates fail to help as many people drop their individual Babadooks as they claim.  That leads to 'drama' (conflict) between autistics arguing about neurodiversity.  Confidentiality conceals the inequities, inequalities and the self-advocacy movement failures.  Confidentiality also privatizes the costs of that change for some people (less intense needs/ not severe disabilities) and socializes the costs for other people (intense needs/severe disabilities).  Some people who need to privatize those costs of improved independent living situations 'get that' and are share their justified resentment for the inequitable help that they still are reluctant to discuss in public discourse.    

Monday, November 8, 2021

rustedaspie was attacked in 2018 by friends of the accounts who in 2020 called Ari N and Steve S part of a 'trifecta of evil"


      Your humble blogger, rustedaspie, was attacked by friends' of twitter accounts of @tclementsuk and @autismgadfly, who later attacked Ari N and Steve S, and has only the screen shots to prove it.  The tweets of the accounts that interacted with my account have been deleted by users or account deletions.  


  I joined a thread that promoted this


Recently, this trend has started to change and there's been a slow growth of autistics who see the problems with neurodiversity.  Writers Tom Clements, Gwen Kansen, and Twilah Hiari have written unfavorable pieces about neurodiversity.  Anorther writer, and twitter user Jonathan Ferguson (AKA One-Tongued Johnny and Wallace Runnymeade) has also spoken out against neurodiversity.  Yuval Levental is another individual who occasionally contributes to the discourse about this loathesome movement and the problems associated with it.  One-Tongued Johnny started a #neurodiversityishistory hashtag, but it's use was noneffective and ephemeral. 


 blog post I quote from above.  Screenshots are posted without links because the other accounts (@tclementsuk) deleted their tweets since June 2018 or the accounts (@YesThatAnna) were suspended. 


This tweet, also shown in the screen shot below, hasn't been deleted.
  https://twitter.com/beingautistic/status/1002867079371018240?s=21


My tweet continues from the screen shot above to the screen shot of the full tweet below. 


   I posted this tweet to sum up what I thought the other accounts were arguing about regarding whether to support the 'neurodiversity' concept as an organizing philosophy. 


  The since-deleted account @onetonguejohnny attacked my account several times based on @onetonguejohnny (Jon Ferguson's) hatred of state attempts to help people in need because of difficulty in obtaining it.  Help was difficult to obtain because of richest people paying news & entertainment media actors & journalists to tell poor white people to hate poor black and brown people.  I call the phenomenon dividing civil rights protected class (disability) by the economic class stratification within the civil rights protected class.  In plain language the political right likes the rich members of all marginalized and oppressed communities to divide the communities from the constituencies that need financial help paying for LTSS in HCBS.  Here are screen shots of his attacks.  


  My reply to the twitter attack from later-suspended account @onetonguejohnny is: Entitlement (earned benefit) is what happens after one is qualified to receive something.  Victimhood is believing one is qualified despite harm until evidence proves one has or hasn't earned the benefit.  The evidence is evaluated by government administrators of the social programs to determine eligibility with the accountability measure of an appeals process.


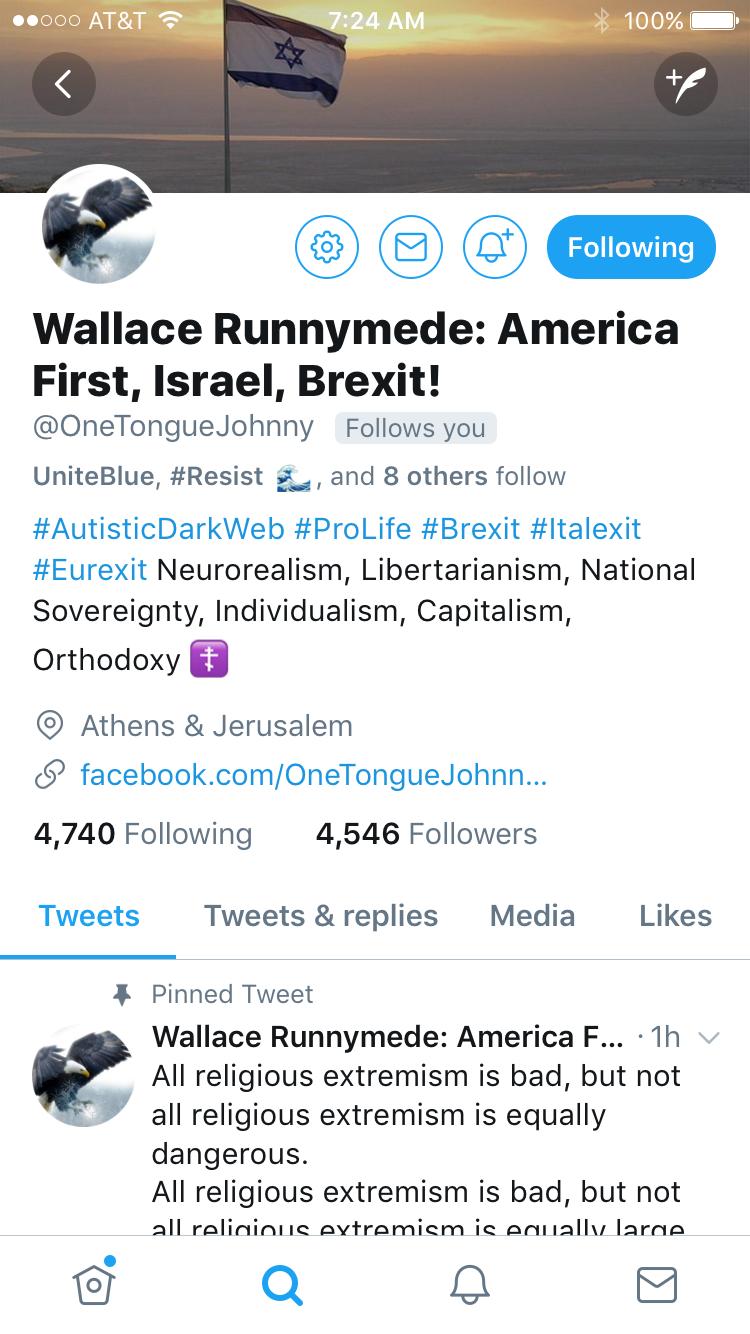
 @onetonguejohnny   as a twitter account was suspended after reports (link might be dead screen shots below of what the tweets showed) of more attacks.  


@onetonguejohnny changed his bio page 


several times before the account was suspended. 

Sunday, November 7, 2021

'alt right' and 'autistic dark web' are mostly Angry White Men who blame the wrong political 'side' for their problems


   The pace of progressive social change to accept, include, accommodate and pay the costs, that individuals cannot pay, in the disability rights movement is savagely unequal.  Those left desperately behind post and say mean things (lash out) 


to those whose 'life journeys' living with a disability have a better quality of life.  Confidentiality conceals the inequities. 


  One such instance of 'lashing out' was in this column by @tclementsuk on twitter.  Fruatration led to a personal attack on Ari Ne'eman and Steve Silberman by @autismgadfly an online 'friend' or 'follower' on twitter of @tclementsuk.  The attack was pushed back on here and here.   


  The second link above, from neuroclastic.com, tried to break down the opponents of the idea of 'neurodiversity' into several groups.  The two groups below

3. The “severe” autism lobby, those promoting a false dichotomy of “mild” and “severe” autism, which primarily leans on the falsehood that non-speaking autistics are severely intellectually disabled. They dehumanize non-speakers by perpetuating misinformed assumptions about their competence and by positing that those with intellectual disability are incapable of self-advocacy or are less human.

4. The anti-neurodiversity movement, many of whose members have been called the “Autistic Dark Web,” a troupe of people who are mostly regarded as trolls and are most visible on Twitter. These people claim that the #ActuallyAutistic/Neurodiversity Movement is full of “social justice warriors” from the far left who want to turn autism into an issue of “identity politics.”

 very well might represent families and friends of people with severe autism who have not progressed as far 'down the path' to full inclusion, acceptance and accommodation in their individually chosen commnunities.  Bad public policy in national, provincial and local governments that inadequately publicizes, funds and delivers LTSS in HCBS is the variable that the 'alt right' or 'autistic dark web' ignores because they don't support a role of government in peoples' lives to help people beyond police, courts and military to protect property and life (in that order).  Confidentiality conceals the inequities and inequalities and prevents the 'scientifically valid' data gathering and sampling.  


  Ari Ne'eman and Steve Silberman were the two people attacked and Ari 'laughed off' the 'trifecta of evil' insult with this tweet deleted since February 2020.  


  Ari Ne'eman further tried to 'laugh off' the attack by joking about his trouble finding a Middle Eastern (including Israeli) food to his liking.  


   This tweet is one


 of the few in the February 16, 2020 thread that hasn't been deleted. 

    Pace of change battles between people who feel they have a worse 'quality of life' who attack those they feel have a better 'quality of life' emerge a lot on social media.  Demands to replace the Affordable Care Act with Medicare for all expanded in benefits and payment rates instead of a 'public option' to buy expanded Medicare instead of private for-profit health insurance are one example.  Demands for free college or a return to more aid that isn't in the form of repayable loans are another public policy example.  People in the 'alt right' or 'autistic dark web' might represent people left behind in the pace of positive social change.  Confidentiality prevents the data-gathering of numbers of people actually helped by activist social movements like the disability rights movement informed by 'neurodiversity.' Being left behind in the progress of positive social change makes individuals vulnerable to extreme right wing political/economic ideologies that have prejudice and hate at their core.  This article is a great read to move the focus back to systemic economics and politics and away from bigoted individuals attacking other individuals in words or with physical weapons.  

Tuesday, October 26, 2021

ADU opponent on twitter 2019 admits earning the six figures of the 'straw man' 'Booz Allen' associate in 2020

 In this link from 2019, the MoCo council passed a law allowing more ADUs (accessory dwelling units-apartments) in basements or yards of single family homes.  


Commenter Kabardino Balkaria (same person as @301lezginka on twitter (formerly @MoCoMillenial on twitter) opposed the law by having County Executive Marc Elrich's back in the 'comment wars' also pasted below.


Kabardino Balkaria could have been letting the perfect be the enemy of the good by pointing out the stormwater runoff and traffic problems from ADUs having off street (bigger driveway) parking.


There is no "me and Elrich" unless you can cite where he is advocating for what I am calling for: YES on ADUs, with incentives to rent them out for under $1500/month. How on earth is this not being for affordable housing.
There was a case where a benevolent woman in Takoma Park rented out an ADU, I think it was a basement apartment for $900/month. This is awesome and there should be more cases like this.
What I am afraid will happen is the following scenario:
a) a wealthy Chevy Chase family who wants to make even more money builds a high-end, freestanding unit on their property and rents it out for $2200/month, which will be out of range for any middle income young renter who takes transit, but will instead go to the Booz Allen associate who brings his car.
b) An entire family moves in with children and vehicles, making the unit functionally a duplex - which would be all well and good, except for the resulting crowded conditions in schools and on roads (since there is no way to prevent the ADU residents from bringing their cars) and increased impermeable surfaces which lowers the quality of life for both the new residents and the existing residents. (So, essentially, when some people are talking about "character of the neighborhood," they are indeed using a racist dogwhistle, and they are factually wrong since the kind of people they fear so much aren't even going to afford to live in the ADUs. But when other people raise "neighborhood" concerns, they really do mean these very unsexy arguments about crowding issues associated with adding more upper-middle-class residents to a single lot.)
My solution? Allow more ADUs, because we aren't going to "build a wall" to keep out new residents and stop growth altogether - but RAISE TAXES on people constructing ADUs for situations A and B, and WAIVE THE TAX for people renting out ADUs for under $1500, to seniors, or to family members.

  Kabardino Balkaria / @MoCoMillenial /@301lezginka trolled council member and ADU supporter (and county executive candidate in 2022) Hans Riemer in this thread with this screen shot in case of tweet or account deletion.  


 Your humble post author replied re whether Marc Elrich is anti business or an exclusionary supporter of owners of existing homes.

 Almost 2 years later in this comment


Wrong.
I’m 32, make six figures in a tech job, have an advanced degree and I pay my damn taxes. I’m a contributing member of society.
I’m a socialist. Experiencing the real world makes you a socialist. These kids aren’t even socialists yet I agree with them. What they say makes sense. Taxes are the price you pay for civilization.


  Kabardino Balkaria also known as @301lezginka (formerly @MoCoMillenial) admits that he or she earns the same income as her or his 'straw man' argument (the Booz Allen associate who can still afford both a car and housing costs) against the ADU zoning law in 2019.  Kabardino Balkaria/ @301lezginka is probably waiting for the apartment they live in to convert to a condo with past rent credited to the purchase.  Marc Elrich has supported that as an affordable housing solution back to when he first ran for council in 2006 and again in 2019 after being elected executive.  


But that is not a sustainable solution either.  Eventually, by aging and dying in place if not job or family situation changes, the first owners of the converted apartment will move out and the resale price won't remain affordable in future markets because the seller will get a profit above paying for moving and a new residence in another location in or outside of Montgomery County.  But enough time (perhaps 10 years or more) will have passed and the resale price will appear to be in line with, or below, the market price in the future.  MPDUs (moderately priced dwelling units) have price caps on resales.  Unfortunately an adequate amount of MPDUs to house all on wait lists need a large amount of total 'market price' units built to produce a small amount to avoid people languishing on a long wait list.  There have been little accountability measures to assess how many wait on lists, for how long, and perhaps get nothing and move out of one county to become another county's 'housing market' 'problem' providing affordable housing.  The displacement happens too slowly and no one puts in the time to gather the data while keeping identities of individuals confidential. That leaves only 'I have a friend' -type anonymous anecdotes driving policy in IRL and social media public discourse more than action making the subject of affordable housing fraught with conflict (drama) that people avoid.   


  Perhaps Marc Elrich's 2006 and 2019 suggestions, amplified on twitter by @301lezginka formerly @MoCoMillenial, for producing and retaining more affordable housing units could be improved by keeping a price cap on condo conversions of apartments built before a certain year (1960?) (like MPDU resales).   An environmental solution to paving the bigger driveways, that could result from adding ADUs in single family detached houses has an easy 'tool' in the 'toolbox' as well.  Require the paving of the driveways with permeable pavement like the parking lot of the Vienna, Virginia community center.  If one has already given up car ownership to avoid living in a car unhoused or long commutes from more affordable 'housing markets' in other jurisdictions the traffic and stormwater runoff 'problems' from unrelated people living together in one single family house are solved without government action.  Homeowners wishing to build an ADU could travel from MoCo to the Vienna community center to learn about permeable pavement as an option, perhaps a requirement, before construction.